Engraftment, Chimerism, and HLA Typing
After a stem cell transplant, whose cells are in the blood? Chimerism testing with informative STR alleles, lineage-specific monitoring, and the HLA typing that matches donors before transplant.
- 5 min
- 6 steps
- 3 questions
- Lesson 59 of 60
In this lesson
- Why chimerism matters
- How chimerism testing works
- Lineage-specific chimerism
- Interpreting results
- HLA typing for transplant
- What to take from this
Picking up where you left off.
Why chimerism matters
After an allogeneic hematopoietic stem cell transplant (HSCT), the recipient’s blood and marrow should be rebuilt from donor cells. A patient whose blood contains a mix of donor and recipient cells is a chimera. Measuring the proportion over time shows:
- Engraftment: donor cells have taken over.
- Graft failure or rejection: recipient cells are returning.
- Relapse: the original malignant (recipient) cells are coming back.
Results guide decisions such as tapering immunosuppression or giving donor lymphocyte infusions.
How chimerism testing works
The standard method uses STRs 1:
- Before transplant, type both donor and recipient at a panel of STR loci.
- Find informative loci, where donor and recipient have different alleles that don’t overlap or stutter into each other, and select a couple for follow-up 1.
- After transplant, amplify the patient’s sample and measure the peak areas of donor-specific and recipient-specific alleles.
- Calculate % donor from the ratio of peak areas, checked against standards made from mixtures of donor and recipient DNA from 0 to 100% donor 1.
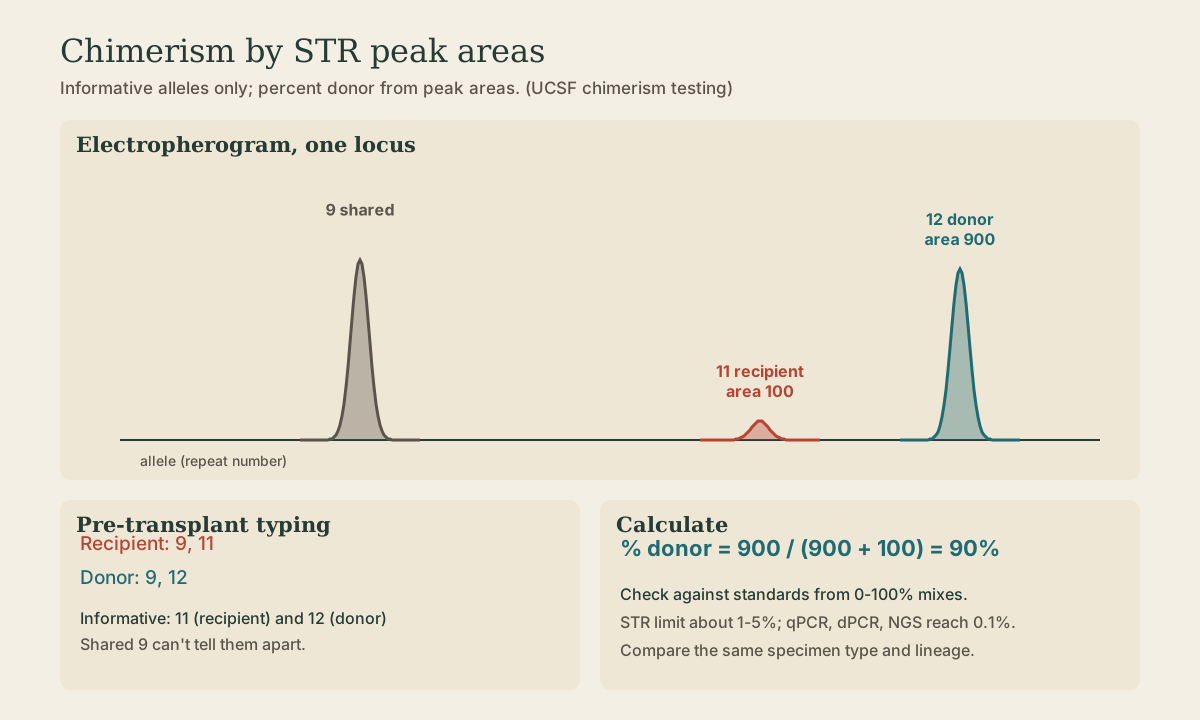
Example: at one locus, recipient 9,11 and donor 9,12. Allele 9 is shared and useless; 11 marks recipient and 12 marks donor. If the 12 peak area is 900 and 11 is 100, the sample is about 90% donor.
STR methods detect a minor population down to about 1 to 5%. Quantitative real-time PCR or digital PCR for insertion-deletion or SNP markers, and NGS, reach 0.1% or lower when earlier warning is needed.
Quick check
Allele 9 is shared. Allele 11 is unique to the recipient and 12 unique to the donor, so both are informative; 12 tracks the donor.
Lineage-specific chimerism
Whole blood is a mix of lineages that engraft and relapse at different rates. Labs often sort cells first (for example CD3+ T cells and myeloid cells, sometimes CD19+ B cells) and test each 1:
- T-cell chimerism matters for graft-versus-host disease, graft-versus-tumor effect, and rejection after reduced-intensity conditioning.
- Lineage of the original disease (myeloid for AML and MDS) is most sensitive for relapse.
Interpreting results
- Full donor (≥95%, depending on the lab’s sensitivity) is the usual goal after myeloablative transplant.
- Mixed chimerism is common early after reduced-intensity transplants and may be stable.
- Falling donor percentage, especially in the disease lineage, warns of relapse or rejection and calls for repeat testing, marrow studies, and MRD markers.
Use the same specimen type and lineage for serial comparisons. Recent transfusions don’t usually interfere (red cells lack nuclei; leukocytes are depleted), but sex-mismatched transplants can also be followed with X/Y FISH.
Quick check
Falling donor chimerism in the lineage of the original leukemia (myeloid for AML) is an early warning of relapse and prompts further testing and intervention.
HLA typing for transplant
HLA (human leukocyte antigen) genes on chromosome 6 encode the molecules T cells use to recognize self. They’re the most polymorphic genes known, with hundreds of alleles per gene 2:
- Class I: HLA-A, -B, -C, on nearly all nucleated cells.
- Class II: HLA-DR, -DQ, -DP, on antigen-presenting cells.
For stem cell transplant, mismatches cause graft rejection and graft-versus-host disease. Unrelated donors are matched at HLA-A, -B, -C, and -DRB1 (an “8 of 8” match), usually adding DQB1 and often DPB1. Siblings share a full HLA set (a haplotype from each parent) with a 25% chance.
Resolution:
- Low resolution (the first field, the allele group, such as A*02) is roughly equivalent to a serological type.
- High resolution (A*02:01) specifies the protein sequence of the antigen-binding region; it’s required for unrelated donor matching.
Methods:
- SSP (sequence-specific primers): PCR primers that amplify only specific alleles.
- SSO (sequence-specific oligonucleotide probes): amplify, then hybridize to probe panels, often on beads.
- SBT (sequence-based typing, Sanger).
- NGS, now standard in many labs, which resolves phase and ambiguous allele combinations.
What to take from this
Chimerism testing measures donor versus recipient cells after transplant using STR loci where their alleles differ; % donor comes from peak-area ratios, sensitive to about 1 to 5%, and qPCR, dPCR, or NGS go lower. Lineage-specific testing (T cells, myeloid cells) is more sensitive for rejection and relapse, and a falling donor percentage in the disease lineage is a warning. HLA typing matches donors at A, B, C, and DRB1 (plus DQB1, DPB1) at high resolution by SSP, SSO, SBT, or NGS.
Practice
Unrelated donor matching focuses on HLA-A, -B, -C (class I) and DRB1 (class II), usually at high resolution, often adding DQB1 and DPB1.
Lesson complete
Nice work.
Sources for this lesson
- 1Chimerism Testing and Engraftment Monitoring. UCSF Immunogenetics and Transplantation Laboratory. verifiedPre-transplant donor and recipient STR typing finds informative loci; post-transplant samples are quantified against donor/recipient mixtures from 0 to 100% donor; lineage-specific (CD3, myeloid) chimerism.
- 2HLA-B gene. MedlinePlus Genetics (National Library of Medicine). verifiedHundreds of HLA-B alleles; HLA-B27 raises ankylosing spondylitis risk (1-5% of carriers develop it); B*57:01 abacavir, B*15:02 carbamazepine, B*58:01 allopurinol reactions.