Leukemia and Lymphoma Markers and Clonality
The fusions and mutations that classify and risk-stratify acute leukemias - PML::RARA, core-binding factor fusions, NPM1, FLT3-ITD - the lymphoma translocations, and how IG/TCR clonality testing tells a lymphoma from a reaction.
- 4 min
- 7 steps
- 3 questions
- Lesson 50 of 60
In this lesson
- Why molecular markers matter
- Acute promyelocytic leukemia
- Acute myeloid leukemia
- Acute lymphoblastic leukemia
- Lymphoma translocations
- Clonality testing
- What to take from this
Picking up where you left off.
Why molecular markers matter
In acute leukemia and lymphoma, specific genetic changes define disease types, predict outcome, select targeted drugs, and provide markers for measurable residual disease (MRD). Many are detected by FISH or karyotype as well as PCR or NGS.
Acute promyelocytic leukemia
APL is defined by t(15;17)(q24;q21), producing PML::RARA, in about 98% of cases 1. The fusion protein blocks differentiation at the promyelocyte stage.
APL is an emergency: patients often have disseminated intravascular coagulation (DIC), and hemorrhage, including into the brain, causes early deaths 1. The fusion also makes APL exquisitely sensitive to all-trans retinoic acid (ATRA) and arsenic trioxide 1, which together cure most patients without chemotherapy. ATRA is started on clinical suspicion, and labs confirm PML::RARA quickly by FISH or RT-PCR. Quantitative PML::RARA RT-PCR is then used for MRD monitoring.
Quick check
APL’s coagulopathy causes early hemorrhagic deaths. ATRA and arsenic trioxide target PML::RARA and are highly curative, so confirming the fusion fast matters.
Acute myeloid leukemia
AML genetics drive risk classification. Under ELN 2022 2:
Favorable
- t(8;21) → RUNX1::RUNX1T1
- inv(16) or t(16;16) → CBFB::MYH11 (these two are the “core-binding factor” leukemias)
- NPM1 mutation without FLT3-ITD
- In-frame bZIP CEBPA mutation
Intermediate
- FLT3-ITD, with or without NPM1, regardless of allelic ratio 2
- t(9;11) → MLLT3::KMT2A
- Changes not classed as favorable or adverse
FLT3 mutations - internal tandem duplications (ITD) and tyrosine kinase domain (TKD) point mutations such as D835 - also select FLT3 inhibitors. The LeukoStrat CDx FLT3 assay is the FDA companion diagnostic for midostaurin, gilteritinib, and quizartinib 3. FLT3-ITD is detected by PCR and fragment analysis: the duplication makes a longer product than the wild type.
Quick check
Favorable: RUNX1::RUNX1T1, CBFB::MYH11, NPM1 without FLT3-ITD, in-frame bZIP CEBPA. FLT3-ITD AML is intermediate regardless of allelic ratio.
Acute lymphoblastic leukemia
- BCR::ABL1 (Ph+ ALL), usually the p190 e1a2 transcript, treated with TKIs plus chemotherapy.
- ETV6::RUNX1 (from t(12;21)), common in childhood ALL, carries a favorable prognosis.
- KMT2A rearrangements, common in infant ALL, carry a poor prognosis.
- MRD after induction, measured by flow cytometry, IG/TCR PCR, or NGS, is one of the strongest predictors of outcome.
Lymphoma translocations
Several B-cell lymphomas join an oncogene to the immunoglobulin heavy chain locus (IGH, at 14q32), placing it under the control of strong B-cell enhancers:
| Translocation | Fusion | Lymphoma |
|---|---|---|
| t(14;18) | IGH::BCL2 | Follicular lymphoma (most cases) |
| t(11;14) | CCND1::IGH | Mantle cell lymphoma |
| t(8;14) | MYC::IGH | Burkitt lymphoma |
The BIOMED-2 primer sets included PCR for t(11;14) and t(14;18) alongside clonality targets 4, though FISH is more commonly used for translocations now.
Clonality testing
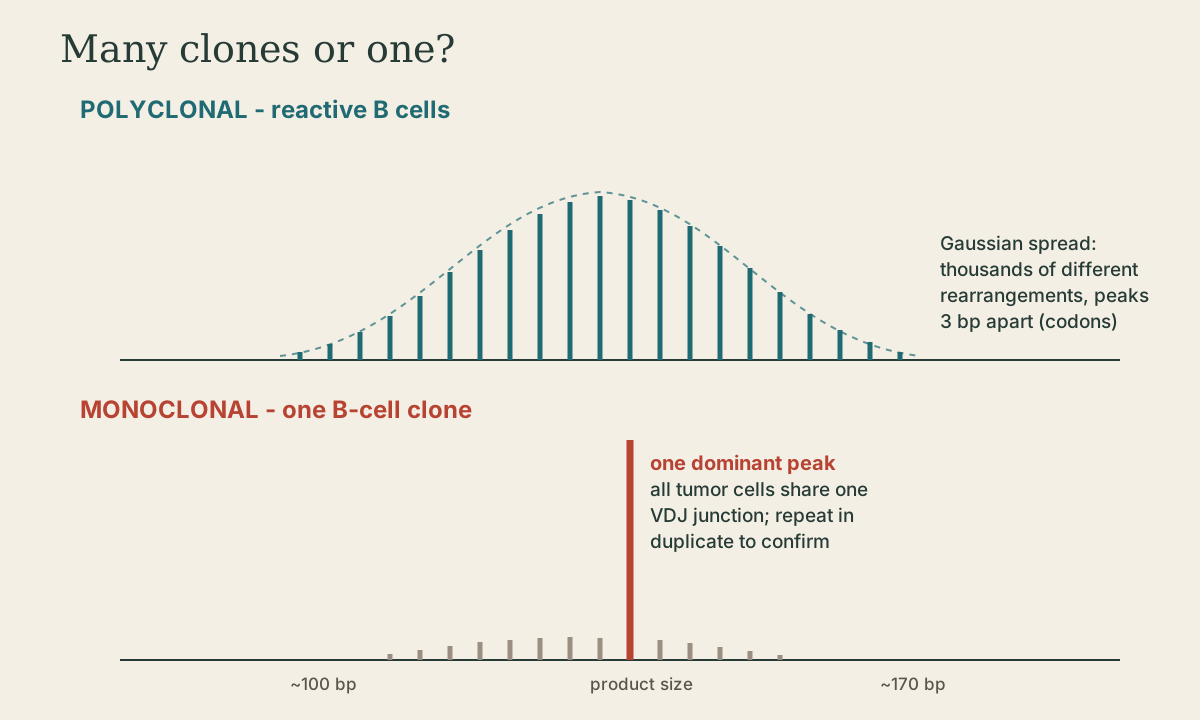
Each B cell rearranges its immunoglobulin genes (IGH, IGK, IGL) and each T cell its T-cell receptor genes (TRB, TRG, TRD) uniquely, joining V, D, and J segments with random nucleotides in between. A reactive population has thousands of different rearrangements; a lymphoma descends from one cell and shares one.
Clonality PCR amplifies across the rearranged junctions with consensus primers, then sizes the products by capillary electrophoresis (“GeneScanning”) or heteroduplex analysis. The standardized BIOMED-2 assays use 107 primers in 18 multiplex tubes covering IGH, IGK, IGL, TRB, TRG, and TRD 4.
- Polyclonal: a bell-shaped (Gaussian) spread of peaks across the size range.
- Monoclonal: one (or two, for two alleles) dominant peak above the background, reproducible in duplicate.
Clonality supports a diagnosis of lymphoma but doesn’t prove it: some reactive conditions produce small clones, and lineage can be misleading (some T-cell lymphomas have IG rearrangements). Results are always interpreted with histology, immunophenotype, and the clinical picture. Next-generation sequencing of IG/TCR rearrangements is increasingly used, and it also gives a patient-specific sequence for MRD tracking.
What to take from this
APL with t(15;17) PML::RARA is an emergency because of DIC, and it’s cured by ATRA plus arsenic. In AML, the core-binding factor fusions, NPM1 without FLT3-ITD, and bZIP CEBPA are favorable under ELN 2022, while FLT3-ITD is intermediate and selects FLT3 inhibitors. ALL markers include BCR::ABL1 p190, ETV6::RUNX1, and KMT2A. Follicular, mantle cell, and Burkitt lymphomas carry IGH translocations with BCL2, CCND1, and MYC. Clonality PCR distinguishes a monoclonal peak from a polyclonal spread and supports, but doesn’t make, a lymphoma diagnosis.
Practice
Polyclonal B cells give a Gaussian spread of sizes; a single reproducible dominant peak indicates a clone. Clonality supports, but doesn’t by itself prove, malignancy.
Lesson complete
Nice work.
Sources for this lesson
- 1Progress and criticalities in the management of acute promyelocytic leukemia. PubMed Central (PMC5725086). verifiedt(15;17) PML::RARA in about 98% of APL; DIC and hemorrhage make it an emergency; exquisitely sensitive to ATRA and arsenic trioxide.
- 22022 ELN recommendations for the diagnosis and management of AML in adults (risk classification summary). AML Hub (summary of Döhner et al., Blood 2022). verifiedFavorable - RUNX1::RUNX1T1, CBFB::MYH11, NPM1 without FLT3-ITD, in-frame bZIP CEBPA; FLT3-ITD is intermediate regardless of allelic ratio.
- 3List of FDA-Authorized Companion Diagnostic Devices (In Vitro and Imaging Tools). U.S. Food and Drug Administration. verifiedExamples include cobas EGFR v2 (exon 19 del, L858R; osimertinib and others), therascreen KRAS (panitumumab, cetuximab, sotorasib), THxID BRAF, Vysis ALK FISH, BRACAnalysis CDx (PARP inhibitors), HER2 FISH, FoundationOne CDx, LeukoStrat CDx FLT3.
- 4J. J. M. van Dongen, et al.. Design and standardization of PCR primers and protocols for detection of clonal immunoglobulin and T-cell receptor gene recombinations in suspect lymphoproliferations: report of the BIOMED-2 Concerted Action BMH4-CT98-3936. Leukemia 17(12):2257-2317. 2003. verified107 primers in 18 multiplex tubes for IGH, IGK, IGL, TRB, TRG, TRD, BCL1-IGH, and BCL2-IGH; clonality read by heteroduplex analysis or GeneScanning.