Hereditary Cancer: BRCA and Lynch Syndrome
Germline cancer predisposition - BRCA1/2, Lynch syndrome's mismatch repair genes, and APC - how tumor screening finds Lynch, why MLH1 methylation and BRAF point to sporadic cancer, and the five-tier language for germline variants.
- 4 min
- 7 steps
- 3 questions
- Lesson 52 of 60
In this lesson
- Germline versus somatic
- BRCA1 and BRCA2
- Lynch syndrome
- Screening tumors for Lynch
- Familial adenomatous polyposis
- Classifying germline variants
- What to take from this
Picking up where you left off.
Germline versus somatic
Hereditary cancer syndromes come from germline pathogenic variants present in every cell from conception. Tumors develop when the second copy is lost or inactivated in a cell (the “two-hit” model for tumor suppressors). Germline testing uses blood or saliva; finding a variant changes screening, surgery, therapy, and testing for relatives.
BRCA1 and BRCA2
BRCA1 and BRCA2 repair DNA double-strand breaks by homologous recombination. Pathogenic germline variants greatly raise the risk of breast and ovarian cancer, and of prostate and pancreatic cancer. Inheritance is autosomal dominant: men and women carry and transmit variants, and each child of a carrier has a 50% chance of inheriting it 1.
- Ashkenazi Jewish ancestry is a risk-assessment criterion 1; three founder variants (BRCA1 c.68_69delAG and c.5266dupC, BRCA2 c.5946delT, long known as 185delAG, 5382insC, and 6174delT) account for most BRCA variants in that population, so targeted founder testing was once common.
- Testing is now usually full sequencing plus deletion/duplication analysis of BRCA1/2 within a multigene panel, since large rearrangements are missed by sequencing alone.
- PARP inhibitors (olaparib, talazoparib, rucaparib) exploit the repair defect; BRACAnalysis CDx is a companion diagnostic for them 2 1.
Quick check
Both men and women carry and transmit BRCA1/2 variants; each child has a 50:50 chance.
Lynch syndrome
Lynch syndrome is the most common hereditary colorectal cancer syndrome, also raising the risk of endometrial, ovarian, gastric, urinary tract, and other cancers. It’s caused by germline pathogenic variants in the mismatch repair (MMR) genes MLH1, MSH2, MSH6, PMS2, or deletions in EPCAM, the gene upstream of MSH2, which silence MSH2 3. It’s autosomal dominant 3.
Without mismatch repair, errors in repetitive DNA accumulate, so Lynch tumors are microsatellite unstable (MSI-high) and lose expression of the affected MMR protein.
Screening tumors for Lynch
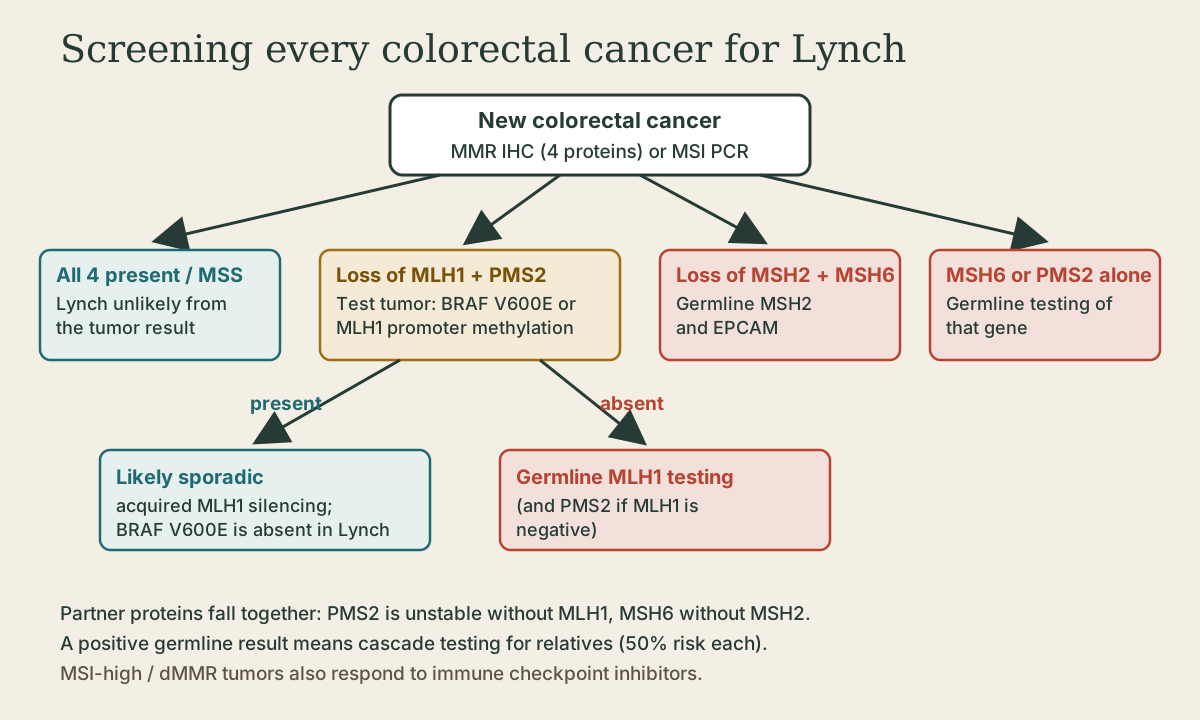
Many centers screen every new colorectal cancer for MMR deficiency by immunohistochemistry for the four MMR proteins or by MSI testing 3. The pattern of protein loss points to the gene:
| IHC loss | Likely gene |
|---|---|
| MLH1 + PMS2 | MLH1 (or sporadic methylation) |
| MSH2 + MSH6 | MSH2 (or EPCAM) |
| MSH6 alone | MSH6 |
| PMS2 alone | PMS2 |
MLH1 and PMS2 travel together (as do MSH2 and MSH6), because PMS2 and MSH6 are unstable without their partners.
The sporadic trap: most MSI-high colorectal cancers with MLH1 loss aren’t Lynch syndrome. They come from hypermethylation of the MLH1 promoter, an acquired change common in older patients, and they often carry BRAF V600E, which is essentially absent in Lynch tumors 3. So MLH1 loss is followed by BRAF V600E or MLH1 promoter methylation testing; if either is present, the cancer is likely sporadic. If neither, germline testing follows.
Quick check
BRAF V600E and MLH1 promoter hypermethylation mark sporadic MSI cancers; BRAF V600E is essentially absent in Lynch syndrome tumors.
Familial adenomatous polyposis
FAP comes from germline APC variants and causes hundreds to thousands of colorectal polyps, with near-certain colorectal cancer without colectomy 3. Other syndromes include Li-Fraumeni (TP53) and MUTYH-associated polyposis (autosomal recessive).
Classifying germline variants
Germline variants are classified in five tiers under the ACMG/AMP standards, using weighted evidence (population frequency, computational predictions, functional studies, segregation in families) 4:
- Pathogenic
- Likely pathogenic
- Uncertain significance (VUS)
- Likely benign
- Benign
Pathogenic and likely pathogenic variants guide management. A VUS doesn’t: care is based on personal and family history, and many VUS are later reclassified, most often to benign. Labs reclassify as evidence accumulates and should have a process for notifying clinicians.
This differs from the four-tier somatic system in the previous lesson; don’t mix the two.
What to take from this
BRCA1/2 and Lynch syndrome are autosomal dominant with a 50% transmission risk. BRCA testing means full sequencing plus deletion/duplication analysis, and PARP inhibitors exploit the repair defect. Lynch syndrome comes from MLH1, MSH2, MSH6, PMS2, or EPCAM; tumors are MSI-high with matching MMR protein loss. MLH1 loss with BRAF V600E or MLH1 promoter methylation is usually sporadic. Germline variants are classified pathogenic, likely pathogenic, VUS, likely benign, or benign, and a VUS shouldn’t drive clinical decisions.
Practice
A VUS lacks evidence either way. Management follows personal and family history, not the VUS, and many VUS are later reclassified as benign.
Lesson complete
Nice work.
Sources for this lesson
- 1Genetics of Breast and Gynecologic Cancers (PDQ) - Health Professional Version. National Cancer Institute. verifiedBRCA1 and BRCA2 are autosomal dominant with a 50% chance of transmission; Ashkenazi Jewish ancestry is a risk-assessment criterion; PARP inhibitors are a therapeutic option.
- 2List of FDA-Authorized Companion Diagnostic Devices (In Vitro and Imaging Tools). U.S. Food and Drug Administration. verifiedExamples include cobas EGFR v2 (exon 19 del, L858R; osimertinib and others), therascreen KRAS (panitumumab, cetuximab, sotorasib), THxID BRAF, Vysis ALK FISH, BRACAnalysis CDx (PARP inhibitors), HER2 FISH, FoundationOne CDx, LeukoStrat CDx FLT3.
- 3Genetics of Colorectal Cancer (PDQ) - Health Professional Version. National Cancer Institute. verifiedLynch syndrome from germline MLH1, MSH2, MSH6, PMS2, or EPCAM variants, autosomal dominant; universal tumor screening by MSI or MMR IHC; MLH1 promoter hypermethylation and BRAF V600E point to sporadic tumors; EPCAM deletions silence MSH2; FAP from APC.
- 4Sue Richards, et al.. Standards and guidelines for the interpretation of sequence variants (ACMG/AMP). Genetics in Medicine 17(5):405-424. 2015. verifiedFive terms for Mendelian variants - pathogenic, likely pathogenic, uncertain significance, likely benign, benign - assigned from weighted evidence codes (very strong, strong, moderate, supporting).