Repeat Expansion Disorders
Fragile X and Huntington disease: repeat-size categories you must know, why repeats expand through mothers or fathers, and how PCR, triplet-repeat-primed PCR, and Southern blot size and characterize them.
- 4 min
- 6 steps
- 3 questions
- Lesson 55 of 60
In this lesson
- Repeats that grow
- Fragile X
- Huntington disease
- Other repeat disorders
- Methods
- What to take from this
Picking up where you left off.
Repeats that grow
Some disease genes contain short repeated sequences that are stable at normal lengths but expand when they pass a threshold, growing larger from one generation to the next. That produces anticipation: earlier onset or more severe disease in successive generations. Testing measures the number of repeats, which places a person in a category.
Fragile X
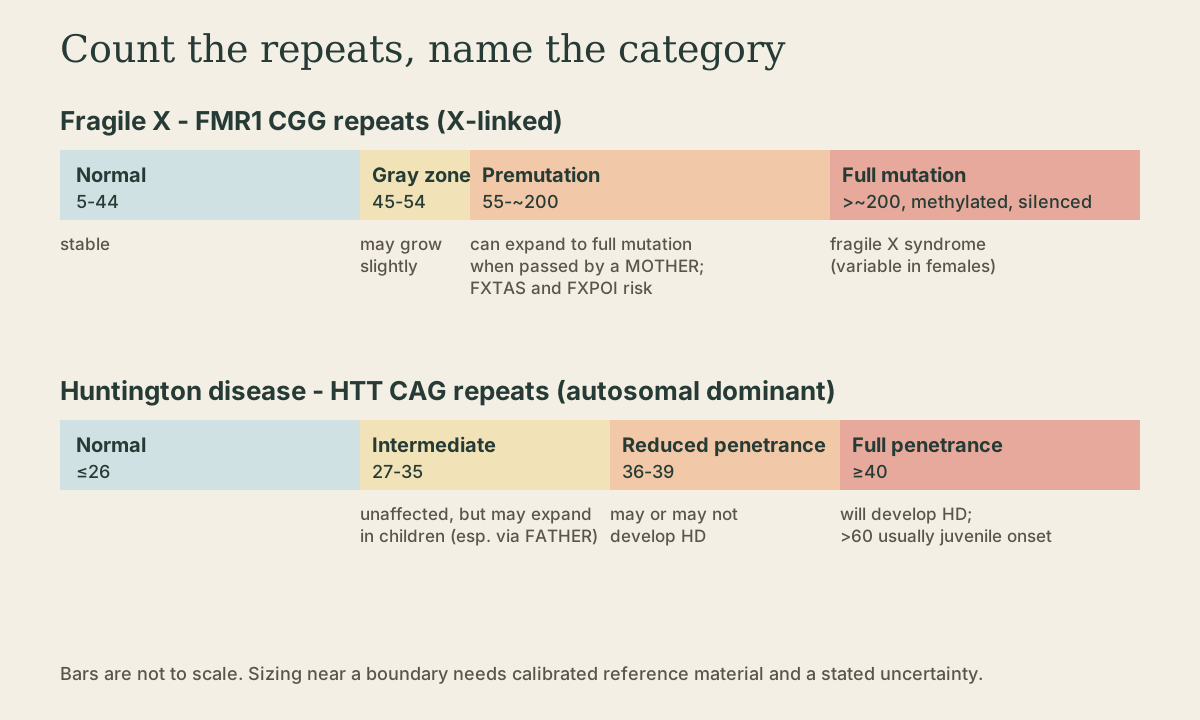
Fragile X syndrome, the most common inherited cause of intellectual disability, comes from expansion of a CGG repeat in the 5’ untranslated region of FMR1 on the X chromosome. When the repeat exceeds about 200, the region becomes methylated and the gene is silenced 1.
Categories (ACMG) 2:
| CGG repeats | Category |
|---|---|
| 5-44 | Normal |
| 45-54 | Intermediate (gray zone) |
| 55-~200 | Premutation |
| >~200 | Full mutation (methylated) |
Key facts:
- Expansion to a full mutation happens through mothers. A woman with a premutation can have children with a full mutation; a man passes his premutation unchanged to all his daughters 1.
- Expansion risk rises with premutation size, and AGG interruptions within the CGG tract lower the risk for premutations of 55 to 90 repeats 2.
- Premutations cause their own conditions: fragile X-associated tremor/ataxia syndrome (FXTAS), mostly in older men, and fragile X-associated primary ovarian insufficiency (FXPOI) 1.
- Females with a full mutation are variably affected because of X inactivation.
Quick check
55 to about 200 is a premutation. Premutations can expand to full mutations when passed from mothers, and carry risks of FXPOI and FXTAS.
Huntington disease
Huntington disease (HD) is an autosomal dominant neurodegenerative disorder from a CAG repeat in exon 1 of HTT, encoding a polyglutamine tract.
Categories 3:
| CAG repeats | Category |
|---|---|
| ≤26 | Normal |
| 27-35 | Intermediate: unaffected, but may expand into the disease range in offspring |
| 36-39 | Reduced penetrance: may or may not develop HD |
| ≥40 | Full penetrance |
Larger repeats bring earlier onset; juvenile HD usually has more than 60 repeats, and repeats tend to grow across generations 4, especially when passed from fathers. A result of 40 or more is fully specific for HD 3.
Predictive testing of healthy at-risk adults is done only with genetic counseling, because there’s no cure, and minors usually aren’t tested for adult-onset disease.
Quick check
36-39 is reduced penetrance. 27-35 is intermediate (unaffected, but may expand in offspring); 40 or more is fully penetrant.
Other repeat disorders
- Myotonic dystrophy type 1: CTG repeat in the 3’ UTR of DMPK; congenital DM1 usually comes through mothers.
- Friedreich ataxia: GAA repeat in intron 1 of FXN, autosomal recessive.
- Spinocerebellar ataxias: several CAG repeat disorders.
Methods
- PCR with fragment analysis across the repeat, sized by capillary electrophoresis, gives exact counts for normal and moderately expanded alleles.
- Large, GC-rich expansions amplify poorly, so a woman who appears to have one normal allele (homozygous? or a hidden expansion?) needs more testing.
- Triplet-repeat-primed PCR (TP-PCR): one primer binds within the repeat at many positions, producing a ladder of products that extends far into large expansions. It detects expansions conventional PCR misses and can show AGG interruptions 2.
- Southern blot with a methylation-sensitive restriction enzyme sizes full mutations and shows methylation, the classic gold standard for fragile X 2. Methylation-specific PCR is an alternative 2.
Repeat sizing needs calibration against sized reference materials, and labs report a size with its measurement uncertainty, which matters at category boundaries.
What to take from this
Fragile X is a CGG expansion in FMR1: normal 5-44, intermediate 45-54, premutation 55-200, full mutation over 200 with methylation. Full mutations arise from maternal premutations, and premutations cause FXTAS and FXPOI. Huntington disease is a CAG expansion in HTT: ≤26 normal, 27-35 intermediate, 36-39 reduced penetrance, ≥40 full penetrance, with expansion more common through fathers. PCR sizes moderate repeats, TP-PCR finds large expansions, and Southern blot shows size and methylation.
Practice
GC-rich full mutations amplify poorly by conventional PCR. Southern blot (with a methylation-sensitive enzyme) shows large expansions and methylation, though triplet-repeat-primed and methylation PCR now cover much of this.
Lesson complete
Nice work.
Sources for this lesson
- 1Fragile X syndrome. MedlinePlus Genetics (National Library of Medicine). verifiedFMR1 CGG repeat normally 5 to about 40; 55-200 is a premutation; more than 200 silences the gene; expansion to a full mutation passes through mothers; premutation raises risk of FXTAS and FXPOI.
- 2ACMG Standards and Guidelines for Fragile X Testing (with 2021 technical standard revision). American College of Medical Genetics and Genomics. verifiedNormal 5-44, intermediate (gray zone) 45-54, premutation 55 to about 200, full mutation over about 200 with methylation; Southern blot and triplet-repeat-primed and methylation PCR; AGG interruptions lower expansion risk for 55-90 repeat premutations.
- 3ACMG technical standards and guidelines for Huntington disease testing. Genetics in Medicine (via Nature). verified26 or fewer CAG repeats normal; 27-35 intermediate (mutable, unaffected); 36-39 reduced penetrance; 40 or more fully penetrant.
- 4Huntington disease. MedlinePlus Genetics (National Library of Medicine). verifiedHTT CAG repeat; 36-39 repeats may or may not cause disease; 40 or more almost always; repeats tend to grow across generations (anticipation); juvenile cases usually more than 60.
Previous: Inherited Thrombophilia: Factor V Leiden and Prothrombin